Inner Elbow Pain From Repetitive Strain
Medial Epicondylalgia | Medial Epicondylitis | Medial Epicondylosis | Golfer's Elbow | Flexor-Pronator Tendinopathy | Common Flexor Tendinopathy
By Brett Becker, MS, OTR/L, ACE-CPT, ACE-GFI
Updated November 5, 2026
Quick answer
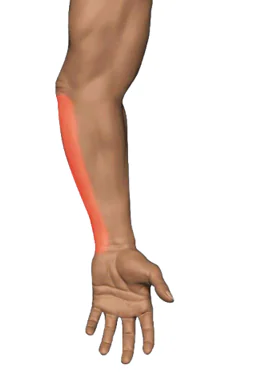
Pain on the inside of your elbow when you grip a mouse, carry a laptop bag, hold your phone up to text, or pick up a full coffee cup. An ache that spreads down the inside of your forearm. Maybe a doctor said "golfer's elbow," and you have never played golf.
Table of Contents
Intro
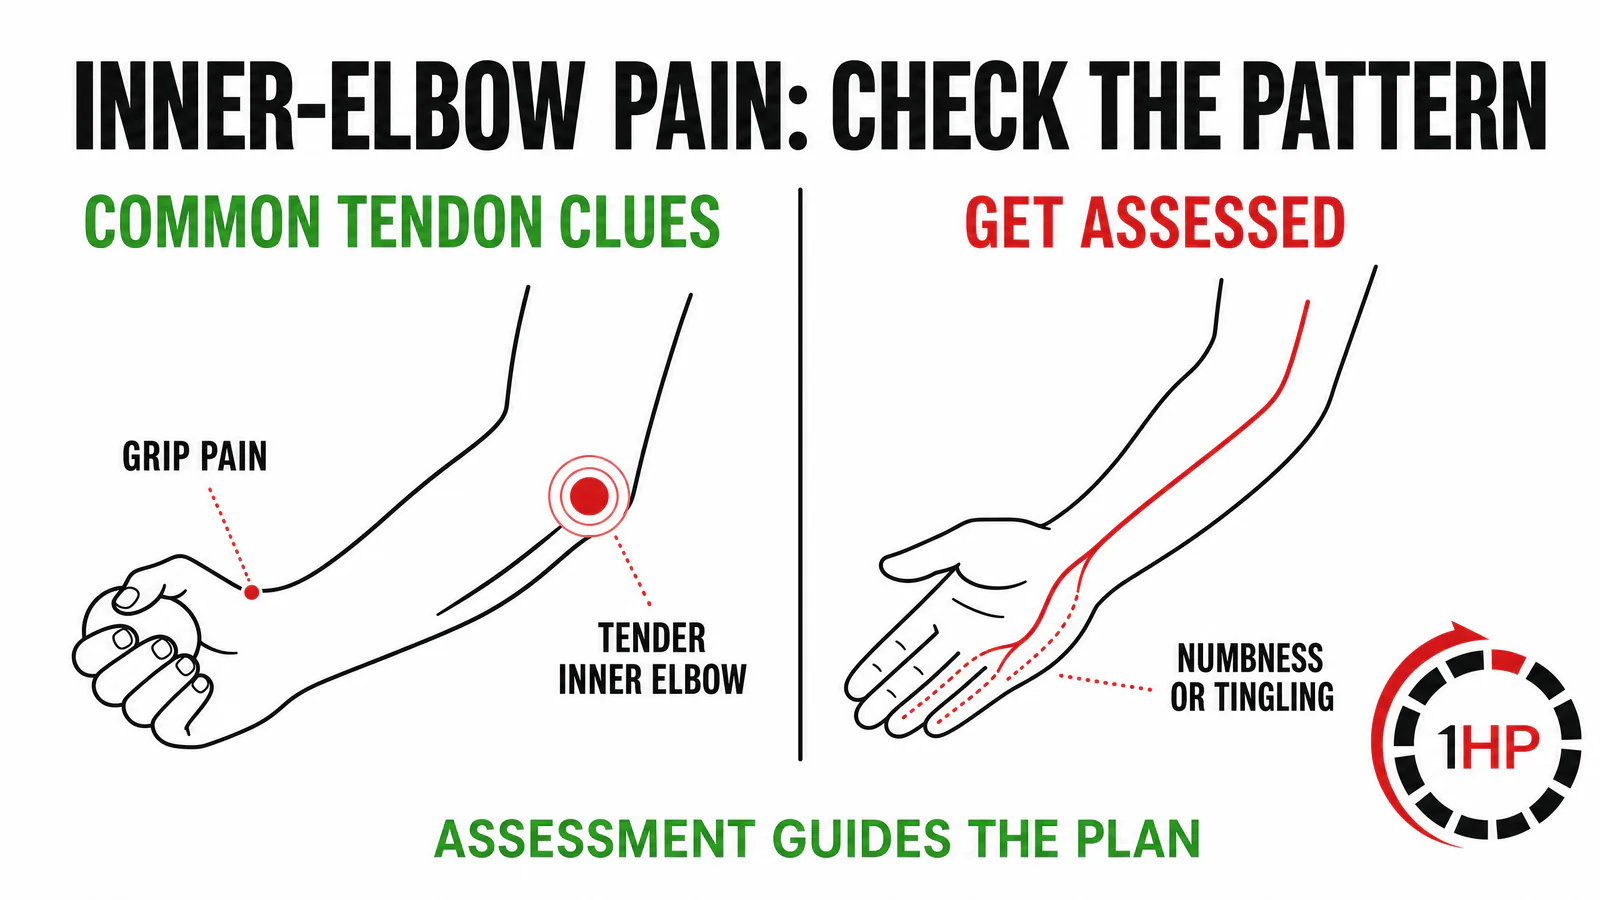
That is normal. Golfer's elbow is a nickname. The real name, medial epicondylalgia, just means pain at the bony bump on the inside of the elbow. That bump is where most of the muscles that bend your wrist and fingers and turn your palm down are anchored. Every grip, click, chord and squeeze pulls on that spot.
It is less common than outer elbow pain. In a Finnish population study, definite medial epicondylitis was found in about 0.4% of adults, compared with 1.3% for the outer elbow [1]. But in people who grip all day, it shows up a lot, and it often gets mixed up with nerve problems at the same spot. This page covers the anatomy, how gripping and computer work load the inner elbow, what happens inside the tendon, how it differs from cubital tunnel syndrome, which tests help, and when our approach does and does not fit.
Disclaimer: The following information is provided for general educational purposes only and should not be considered medical advice. It is not intended to replace consultation with a qualified healthcare professional. If you have specific concerns or questions about your health or medical condition, please seek the guidance of a licensed physician or another qualified medical practitioner. Any reliance you place on the information provided is solely at your own risk. In no event will the author or 1HP be liable for any loss or damage arising from using this information. Always consult with a healthcare professional before starting or changing any medical treatment or regimen.
What 1HP's 2026 Data Shows for Inner-Elbow Pain
The 1HP intake body map did not ask about the elbow as a separate region, so The 1HP Wrist and Hand Pain Report 2026 does not provide an inner-elbow prevalence estimate. Its applicant data does show how often related labels appeared: among 1,023 coaching applicants, 7 named golfer's elbow, and 1 said a doctor or test had confirmed it.
The same chapter found that 84 applicants named at least one tendon condition and 67 named at least one nerve condition. It also recorded cubital tunnel and other ulnar nerve labels, which can produce symptoms near the same side of the elbow. These are minimum counts from written applications, not diagnoses made by 1HP. They support checking whether the pattern is flexor-tendon pain, ulnar nerve irritation or another cause before choosing a capacity approach.
Anatomy and Physiology of the Inner Elbow
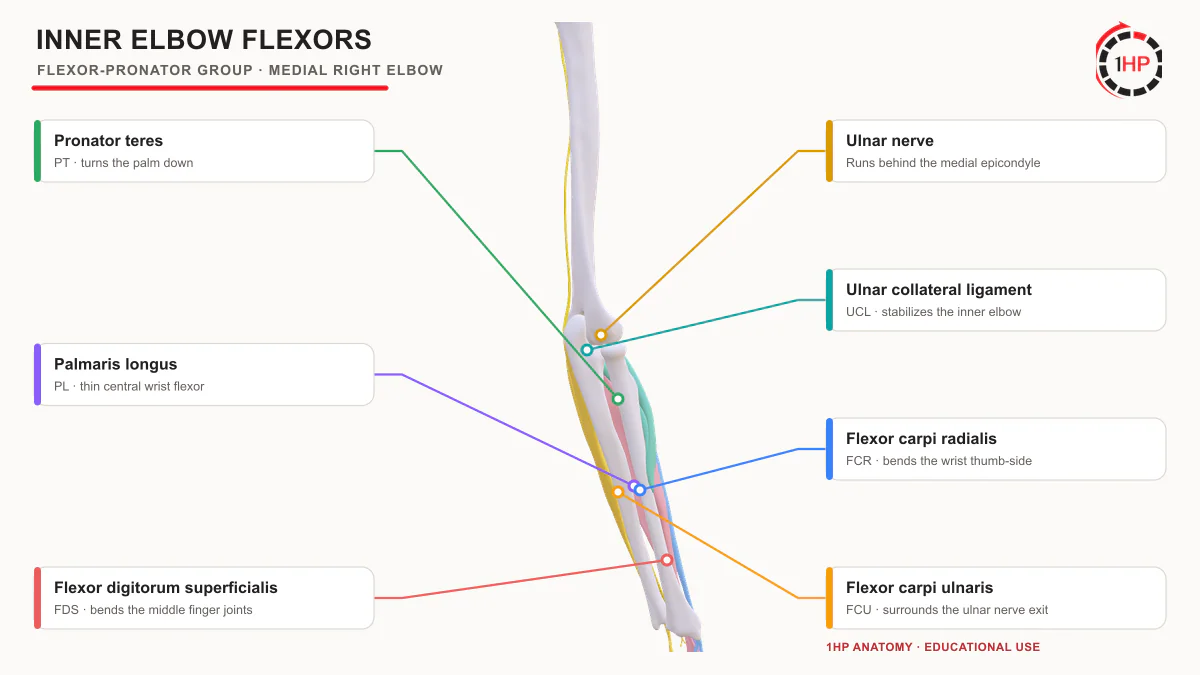
The bony bump on the inside of your elbow is the medial epicondyle of the humerus (upper arm bone). Five muscles share a common tendon that starts here. Together they are called the flexor-pronator group [2]:
- Pronator teres: Turns the palm down (pronation).
- Flexor carpi radialis (FCR): Bends the wrist toward the palm and tips it toward the thumb.
- Palmaris longus: Helps bend the wrist. About 15% of people do not have one.
- Flexor carpi ulnaris (FCU): Bends the wrist and tips it toward the pinky. The ulnar nerve passes between its two heads.
- Flexor digitorum superficialis (FDS): Bends the middle knuckles of the fingers.
The tendon most often involved is the shared origin of the pronator teres and FCR.
Two other structures sit right next to this tendon:
- The ulnar collateral ligament (UCL), which stabilizes the inside of the elbow.
- The ulnar nerve, which runs in a groove behind the medial epicondyle, the "funny bone." This is why inner elbow tendon pain and ulnar nerve symptoms often travel together.
Biomechanics: Why the Inner Elbow Takes the Load
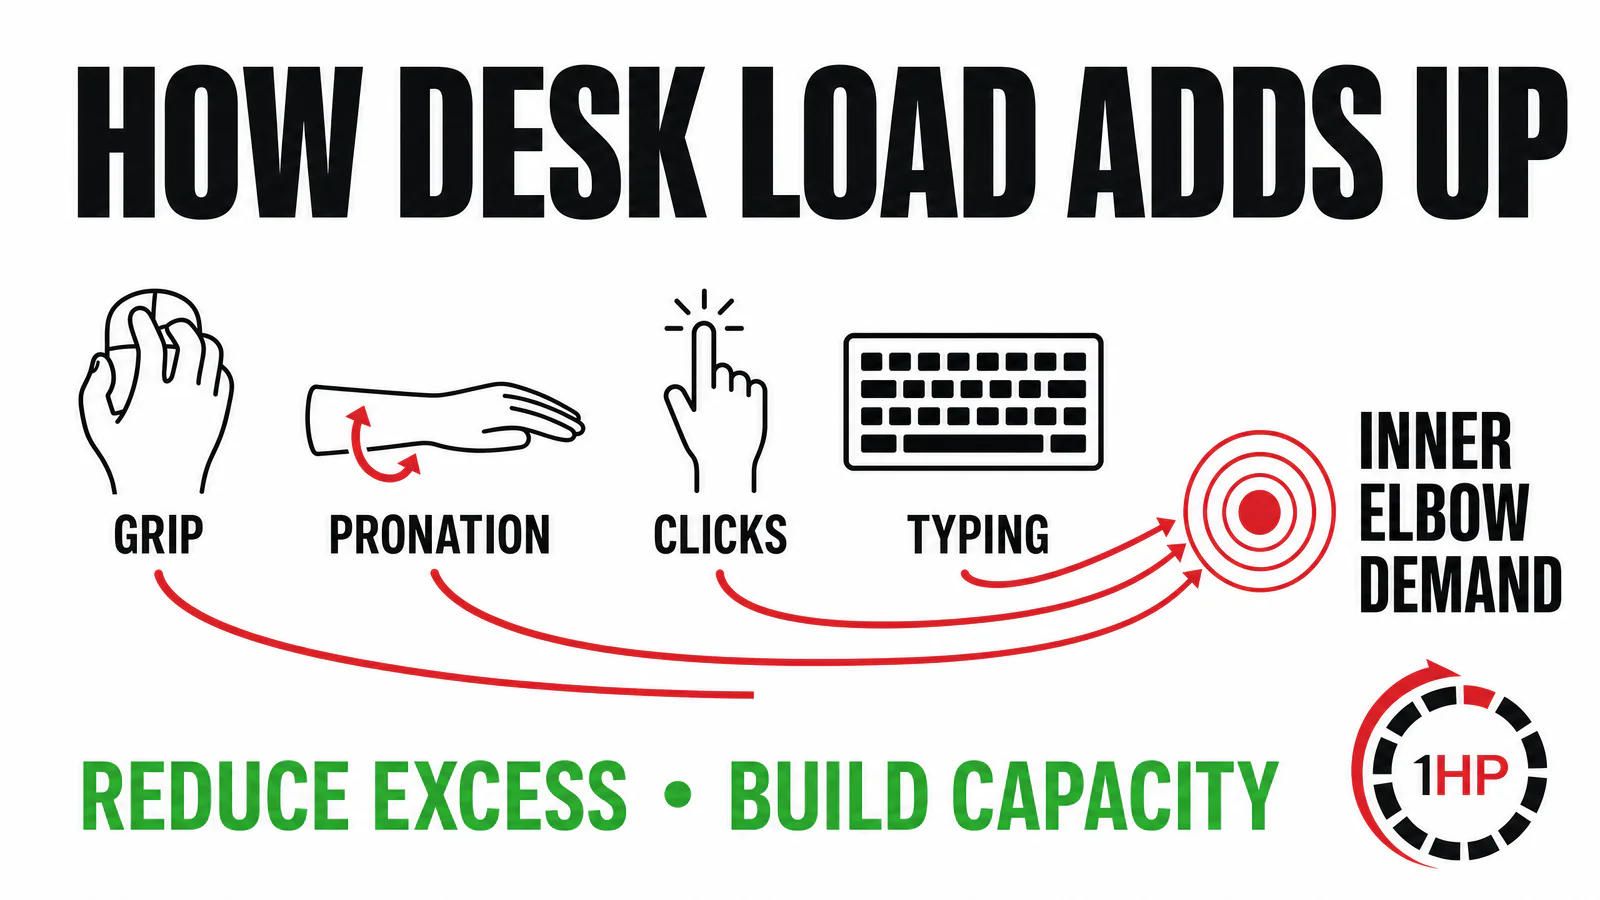
- Grip force travels up the arm. When you squeeze a mouse, phone, pen, tool or bar, the flexor muscles pull on their tendon at the elbow. The harder and longer the grip, the more load at the origin.
- Palm-down rotation adds load. Typing and mousing happen with the palm down, which keeps the pronator teres switched on.
- Wrist bending toward the palm. Repeated wrist flexion, like clicking with the wrist or flicking a stylus, adds more pull.
- Static gripping is work. Holding a phone in front of your face, or keeping a firm hold on a mouse for hours, keeps the same low-level muscle activity going with little rest [3].
- Stress grip. People squeeze harder when they are stressed or focused. More grip force than the task needs means more load at the elbow.
How Repetitive Strain Causes It (Functional Mechanisms)
- Mouse and trackpad work. A firm grip, constant clicks, palm down all day.
- Phone use. Holding the phone up with a bent elbow and a gripping hand.
- Drawing and stylus work. A tight grip held for hours.
- Instruments. Guitar fretting, violin and viola, drumming and wind instruments that support weight with the hands.
- Hands-on jobs. Dental work, surgery, massage, hairstyling, restaurant servers carrying plates palm up.
- Lifting and climbing. Rows, pull-ups, curls, deadlifts and climbing grips load the same muscles hard. Smoking, obesity, repetitive movements and forceful work have all been linked to medial epicondylitis in population data [1].
- Gaming after work. Arcade sticks, controllers and mice with a tight grip add hours of load after the workday.

Pathophysiology: The Tendinopathy Spectrum and the Healthbar
The Healthbar
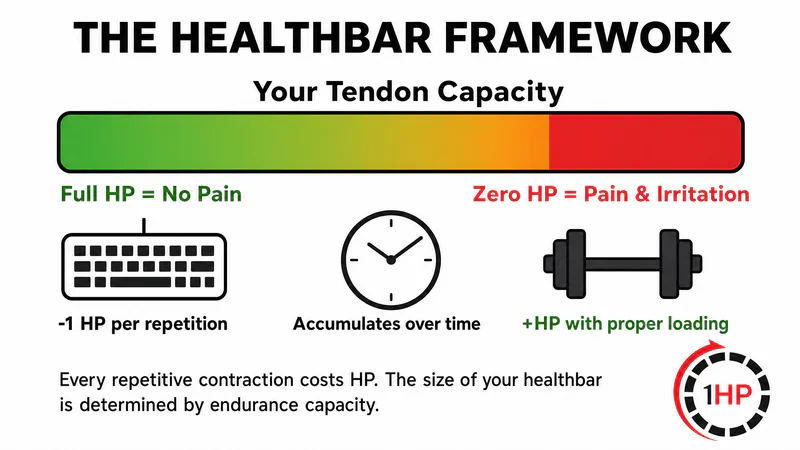
- Your flexor-pronator tendon has a healthbar. The size is its endurance capacity.
- Every grip, click and palm-down hold drains HP. A looser grip, a mouse that fits, and phone stands lower the drain.
- Breaks and sleep refill HP.
- When HP hits zero, you feel pain at the inner elbow during the task and an ache afterward.
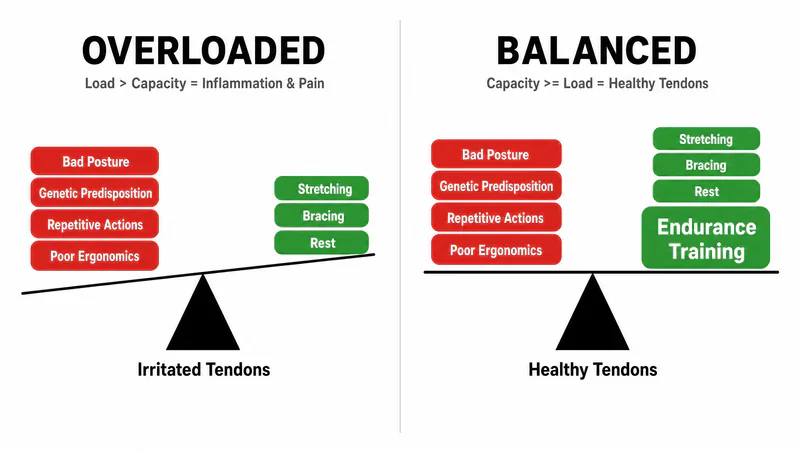
Load > Capacity = Pain.
Inside the Tendon
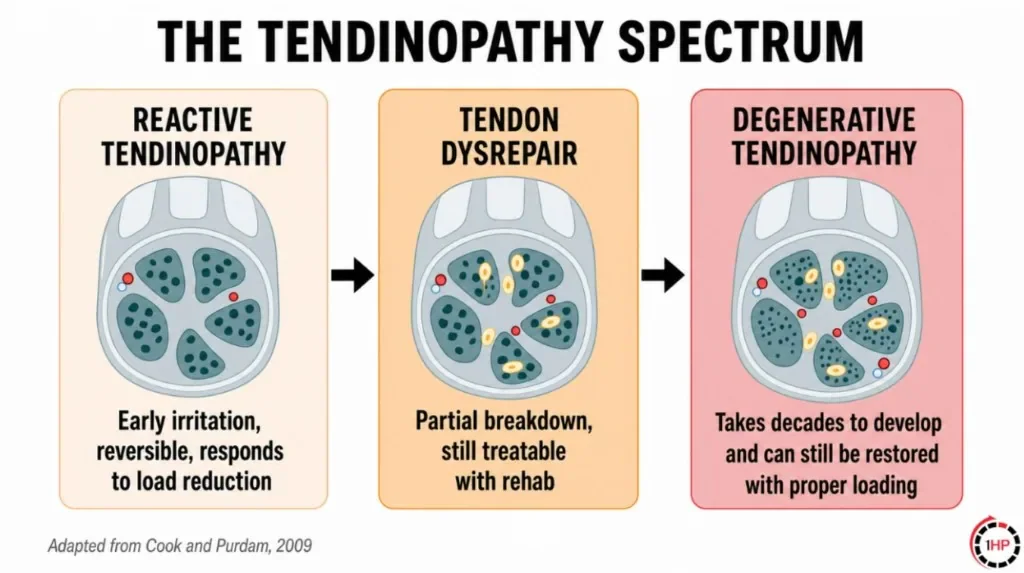
When surgeons examine painful elbow tendons, they find disorganized collagen, new blood vessels and fibroblast cells, but not the inflammatory cells you would expect from "-itis." This pattern was described in detail for both outer and inner elbow tendinosis [4]. That is why the newer names "epicondylalgia" and "epicondylosis" are more accurate than "epicondylitis."
Tendon problems happen along a continuum [5, 6]:
- Reactive: A fast response to a jump in load, like a new lifting program or a heavy project. The tendon swells and hurts.
- Disrepair: Ongoing overload makes the tendon more disorganized. Still trainable.
- Degenerative: Long-term changes in parts of the tendon. The healthy tissue around them can still be trained.
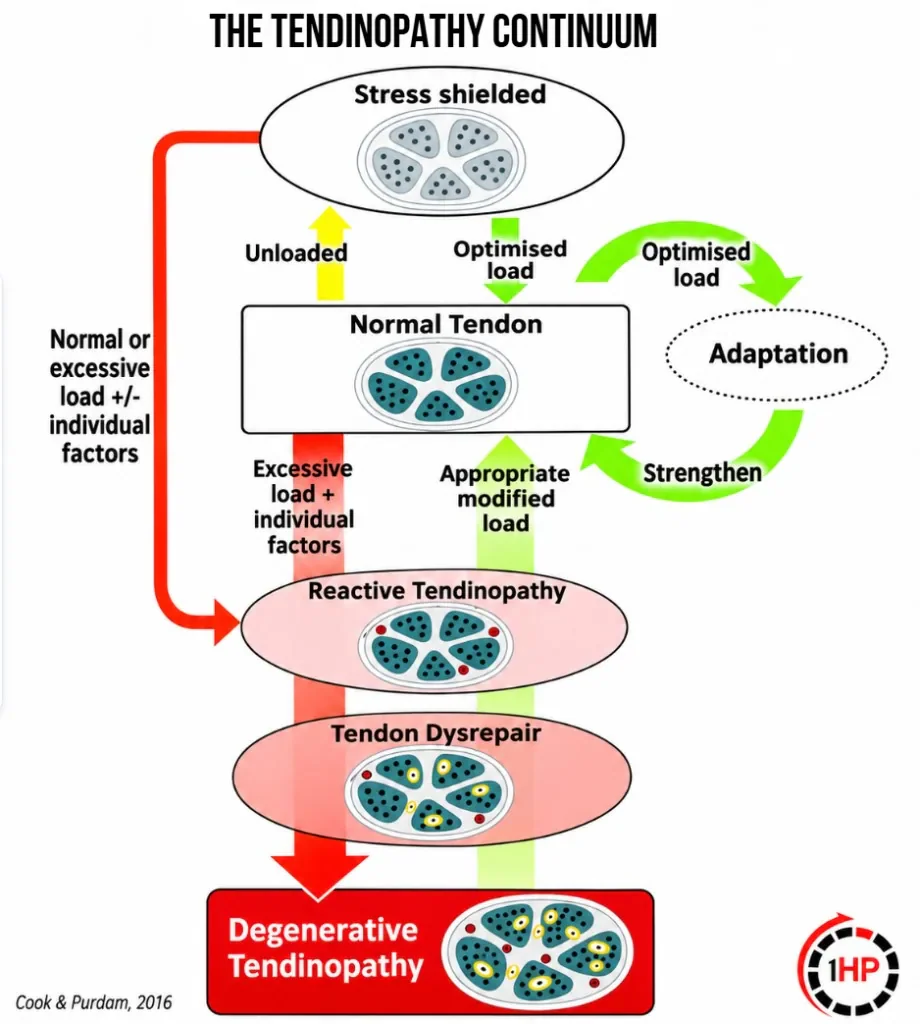
A tendon can move both ways along this path, and an old problem can flare on top of itself [6]. After each heavy session, tendon collagen breaks down faster than it rebuilds for roughly the first day before recovery catches up [7]. Without enough recovery, the balance tips toward breakdown.
Load, Imbalance and Load Modification
- Volume: Total grip time and grip force per day.
- Compression and tension at the bone: The tendon is pulled hardest where it attaches to bone, and compressed with some elbow and wrist positions [8].
- Imbalance: Low endurance in the flexors, weak extensors, and weak shoulder and upper back muscles push more work onto the forearm.
Load modification means lowering the drain enough to stop the flare cycle, without stopping work, while you build capacity.
Additional Pathophysiology
Ulnar nerve irritation. The ulnar nerve runs right behind the medial epicondyle and between the two heads of the FCU. Tight, overworked flexor muscles and a bent elbow can irritate it, causing tingling in the ring and small fingers. Inner elbow tendinopathy and ulnar nerve symptoms often show up together. See cubital tunnel guide.
Median nerve at the forearm. The median nerve passes between the two heads of the pronator teres. Overload of this muscle can irritate the nerve (pronator syndrome), causing aching in the forearm and tingling in the thumb side fingers.
Sensitization. Long-standing pain can make the nervous system more protective. See Why Fear Keeps your Wrist Pain (RSI) From Recovering.
Differential Diagnosis
Differential diagnosis means comparing tendon, nerve, ligament, joint, and neck problems that can all produce inner-elbow or forearm symptoms. Pain with gripping is different from true finger numbness, instability, locking, or a snap, and those differences guide the next step.
| Condition | Clues |
|---|---|
| Cubital tunnel syndrome | Tingling or numbness in the ring and small fingers, worse with the elbow bent, positive Tinel's sign behind the elbow. See cubital tunnel guide |
| Ulnar collateral ligament (UCL) injury | Pain on the inside of the elbow with overhead throwing or a fall, pain with sideways stress on the elbow, possible instability |
| Pronator syndrome | Forearm ache plus tingling in the thumb, index and middle fingers, including the palm. See carpal tunnel guide |
| Cervical radiculopathy (C8 or T1) | Neck pain, symptoms along the inner arm and hand that change with neck movement |
| Medial elbow arthritis or loose bodies | Stiffness, locking or catching, loss of motion, often with a history of injury |
| Snapping triceps or ulnar nerve subluxation | A snap on the inner elbow when bending and straightening |
| Palm side wrist tendinopathy | Pain lower on the forearm and wrist rather than at the elbow. See palm side wrist pain guide |
| Thoracic outlet syndrome | Symptoms across the whole arm, worse with arms overhead. See arm and hand numbness guide |
Where the 1HP Approach Fits
- Often a fit: Gradual, load-related medial epicondylalgia or palm-side wrist tendinopathy without instability or progressive nerve loss. Capacity coaching can build flexor-pronator endurance and grade the return to gripping, typing, lifting, and sport.
- May fit after assessment: Mild cubital-tunnel or pronator-syndrome patterns can be load-sensitive, but numbness means the nerve source and severity should be checked first. Thoracic-outlet symptoms use a different capacity plan.
- Medical assessment first: A traumatic UCL injury, elbow instability, arthritis or loose bodies, or objective weakness from a cervical nerve problem needs medical evaluation.
- Snapping needs a distinction: Tight tissue can add irritation, but a snapping triceps or an ulnar nerve that visibly moves over the bone can reflect structural instability. Endurance training does not reposition an unstable nerve or tendon.
Common Misdiagnoses
1. "It's cubital tunnel" (or "It's just golfer's elbow"). These two often coexist. Inner elbow pain with pain on resisted wrist flexion and palm-down rotation points to the tendon. Tingling or numbness in the ring and small fingers points to the nerve. Treating only one when both are present is a common reason for slow progress.
2. "You don't play golf, so it can't be golfer's elbow." The nickname is misleading. Computer work, phone use, music and lifting all load the same tendon. See Computer-Related Golfer's Elbow.
3. "It's inflamed, so rest and anti-inflammatories." The tissue shows structural change without inflammatory cells [4]. Rest helps symptoms but does not rebuild capacity. See Rest Is One Reason Your Elbow Pain Never Heals.
4. "Your MRI shows tendon changes, so the tendon is damaged." Tendon changes are common and do not predict pain well. Healthy tendon around the changed area can still be trained.
Medical Tests That Confirm or Rule Out a Misdiagnosis
- Diagnostic ultrasound: Shows tendon thickening and changes at the common flexor origin, and can check the ulnar nerve for swelling or slipping out of its groove.
- MRI: For suspected UCL tears, partial tendon tears, bone bruising or loose bodies.
- X-ray: For arthritis, bone spurs or loose bodies.
- Nerve conduction study and EMG: If there is numbness, tingling or weakness in the hand, to check the ulnar and median nerves.
- Neck evaluation: If symptoms change with neck movement.
See Your Scan Is Looking at the Wrong Thing for Elbow Pain.
How 1HP Screens Capacity (Our Testing Philosophy)
- Load story: Mouse, phone, stylus and instrument hours, grip habits under stress, lifting and climbing, and next-day response.
- Symptom mapping: Inner elbow pain, forearm ache, or tingling in the ring and small fingers or the thumb side fingers.
- Physical therapy special tests: Resisted wrist flexion and resisted pronation with the elbow straight, palpation at the medial epicondyle, a passive medial epicondylitis test, valgus stress tests for the UCL, the elbow flexion test and Tinel's test for the ulnar nerve, a pronator syndrome screen, and a neck screen.
- Pain-free grip strength: How hard you can squeeze before pain starts, compared side to side, with the elbow bent and straight.
- Endurance capacity testing: Wrist flexion and forearm pronation with a light weight scaled to your body weight, paced by a metronome until fatigue or symptoms show up. Timed isometric holds at moderate effort. Side-to-side comparison and our coaching targets, which are experience-based guides, not published norms.
- Activity tolerance and 24-hour response.
Commonly Prescribed Treatments: What Works and What Doesn't
| Treatment | What the evidence says | Where it fits |
|---|---|---|
| Cortisone injection | In a randomized, double-blind trial, injection reduced pain at 6 weeks but gave no added benefit at 3 months or 1 year [9]. Injecting near the ulnar nerve carries extra risk | Short-term relief only |
| Counterforce strap | Some people feel less pain with a strap just below the inner elbow. It does not build capacity, and it should not press on the ulnar nerve. See Your Elbow Strap Hides the Problem. It Doesn't Fix It! | Comfort aid during heavy tasks |
| Wrist splint | Rests the wrist flexors but weakens them over time [10] | Short term during a severe flare |
| NSAIDs | Short-term pain relief | Occasional use |
| Rest | Symptoms ease, then return with load | Short load reduction |
| PRP and other injections | Mixed evidence across elbow tendon problems. See Stem Cell Therapy for Tendonitis in Wrist and Hand: 2026 Evidence | Not first line |
| Surgery | Considered after long, failed conservative care. Results tend to be worse when the ulnar nerve is also involved [14] | Last resort |
| Progressive loading | Exercise-based care is the standard conservative approach, and tendons adapt to the right repeated load [11] | The core of the plan |
What 1HP Recommends
We use the Load Reset Framework: Reset Load, Activate with Isometrics, Build Endurance and Progress.
Step 1: Reset load.
- Loosen your grip. Use the lightest grip the task needs. See 3 Tips to Stop Death Gripping Your Mouse.
- Use a phone stand instead of holding the phone up with a bent elbow.
- During a flare, use lifting straps or hooks for pulling exercises, and swap straight-bar curls for neutral-grip variations.
- Manage stress grip. Stress raises grip force and tension. See Cortisol & Wrist Pain.
- Keep symptoms at about 3 to 4 out of 10 or less, settling by the next morning [12].
Step 2: Activate with isometrics.
- Wrist flexion and pronation holds against light resistance with the elbow bent, then straight, about 45 seconds, 3 sets, at a moderate effort, about half to seven tenths of your maximum.
- Isometrics ease pain for some people. Research shows the effect varies [13].
Step 3: Build endurance and progress.
- High-repetition, light-weight wrist flexion, pronation and grip work, paced by a metronome.
- Add the wrist extensors and the shoulder and upper back so the forearm is not doing all the work.
- Progress reps first, then weight, then elbow position (bent to straight), then real tasks.
Step 4: Support tools.
- Wrist Flexor Stretch, Anterior Forearm Massage, ulnar nerve glides if tingling is present, and heat before long sessions.
What to expect. Elbow tendons are slow adapters. Many people notice change in 4 to 8 weeks, and lasting tendon change often takes about 12 weeks or more of steady loading [11]. Early soreness is normal. Sharp pain above about 5 to 6 out of 10, weakness, or symptoms that last into the next day mean scale back.

Is This Approach Right for You?
Likely a good fit:
- Inner elbow pain that rises with gripping, mousing, phone use, playing or lifting and eases on lighter days.
- Pain on resisted wrist flexion or palm-down rotation.
- Normal imaging or tendon changes without a large tear.
- You have tried rest, a strap or an injection and it came back.
Likely NOT a good fit (or not first):
- A sudden "pop" or injury with bruising, or pain after a throw. Rule out a UCL tear or tendon rupture.
- A loose or unstable elbow.
- Locking or catching that suggests a loose body in the joint.
- Constant numbness, hand weakness or muscle wasting between the thumb and index finger. That points to significant ulnar nerve involvement and needs a doctor.
- Several recent cortisone injections into the same tendon. Get medical guidance on how much load the tendon can safely take.
Red Flags: When to See a Physician
See a doctor before starting if you have:
- Constant numbness that does not change with activity
- Worsening weakness or clumsiness in the hand
- Visible muscle wasting in the hand
- Major swelling or color change
- A recent injury, fall or pop
- Fever, redness or heat
- Severe, unrelenting pain
- Symptoms that wake you every night
- An elbow that locks or will not straighten
Seek urgent care for a deformed elbow after a fall or a hot, red, swollen elbow with fever.
Frequently asked questions
Is inner elbow pain golfer's elbow or cubital tunnel?
It can be one or both. Pain with gripping and palm-down turning points to the tendon. Tingling in the ring and small fingers points to the ulnar nerve. A good exam checks both.
Does an elbow strap help?
It can reduce pain during heavy tasks for some people. It does not fix the underlying capacity problem, and it should not press on the nerve behind the elbow.
Can stress make inner elbow pain worse?
Yes. Stress raises grip force and muscle tension, which increases load on the tendon.
Should I stop lifting weights?
Usually not. Lower grip-heavy volume during a flare, use straps for pulls, choose neutral grips, and build back gradually.
Why does my inner elbow hurt when I hold my phone?
Holding a phone uses a gripping hand and a bent elbow, which keeps the flexor-pronator muscles working the whole time. A phone stand and endurance work both help.
References
- Shiri R, Viikari-Juntura E, Varonen H, Heliövaara M. Prevalence and determinants of lateral and medial epicondylitis: a population study. Am J Epidemiol. 2006;164(11):1065-1074.
- Reece CL, Susmarski AJ. Medial Epicondylitis. In: StatPearls. Treasure Island (FL): StatPearls Publishing; updated 2023.
- Visser B, van Dieën JH. Pathophysiology of upper extremity muscle disorders. J Electromyogr Kinesiol. 2006;16(1):1-16.
- Kraushaar BS, Nirschl RP. Tendinosis of the elbow (tennis elbow). Clinical features and findings of histological, immunohistochemical, and electron microscopy studies. J Bone Joint Surg Am. 1999;81(2):259-278.
- Cook JL, Purdam CR. Is tendon pathology a continuum? Br J Sports Med. 2009;43(6):409-416.
- Cook JL, Rio E, Purdam CR, Docking SI. Revisiting the continuum model of tendon pathology. Br J Sports Med. 2016;50(19):1187-1191.
- Magnusson SP, Langberg H, Kjaer M. The pathogenesis of tendinopathy: balancing the response to loading. Nat Rev Rheumatol. 2010;6(5):262-268.
- Cook JL, Purdam C. Is compressive load a factor in the development of tendinopathy? Br J Sports Med. 2012;46(3):163-168.
- Stahl S, Kaufman T. The efficacy of an injection of steroids for medial epicondylitis. A prospective study of sixty elbows. J Bone Joint Surg Am. 1997;79(11):1648-1652.
- Magnusson SP, Kjaer M. The impact of loading, unloading, ageing and injury on the human tendon. J Physiol. 2019;597(5):1283-1298.
- Bohm S, Mersmann F, Arampatzis A. Human tendon adaptation in response to mechanical loading: a systematic review and meta-analysis. Sports Med Open. 2015;1(1):7.
- Silbernagel KG, Thomeé R, Eriksson BI, Karlsson J. Continued sports activity, using a pain-monitoring model, during rehabilitation in patients with Achilles tendinopathy. Am J Sports Med. 2007;35(6):897-906.
- Clifford C, Challoumas D, Paul L, Syme G, Millar NL. Effectiveness of isometric exercise in the management of tendinopathy. BMJ Open Sport Exerc Med. 2020;6(1):e000760.
- Gabel GT, Morrey BF. Operative treatment of medial epicondylitis. Influence of concomitant ulnar neuropathy at the elbow. J Bone Joint Surg Am. 1995;77(7):1065-1069.